
Medical Tourism Blog
Inlay Filling in Korea: Materials, Treatment Steps, Recovery and Travel Planning

Table of contents
- Inlay Filling at a Glance
- What Is an Inlay Filling?
- Who Is a Good Candidate for an Inlay Filling?
- How Is an Inlay Filling Performed?
- Why Visit Korea for an Inlay Filling?
- Key Information for International Patients
- Which Are the Best Clinics in Korea for Inlay Filling?
- How Much Does an Inlay Filling Cost in Korea?
- Inlay Filling From Start to Finish
- Alternatives to an Inlay Filling
- How Can I Prepare for an Inlay Filling?
- Aftercare Advice
Considering treatment in Korea? Everything you need to know e.g. — how to avoid scams, visas, interpreters, recovery tips — in our Medical Tourism Master Guide. Plan with confidence in minutes, not weeks!
Last updated: September 2026
Inlay Filling at a Glance
- What it is — An inlay is a custom indirect filling made outside the mouth and bonded or cemented into a prepared cavity; unlike an onlay, it does not cover the tooth’s cusp tips.
- Best candidates — It is suited to a premolar or molar with moderate decay or a failed filling that is too extensive for a predictable direct resin filling but still has strong, intact cusps and enough healthy tooth structure.
- Korea cost — Inlay fillings in Korea are listed at ₩400,000–₩600,000, approximately US$300–$400; ask whether diagnostics, a temporary, CAD/CAM or laboratory fabrication, bonding, and bite reviews are included.
- Visits and travel — Plan 3–5 business days for a laboratory-made inlay; chairside CAD/CAM may allow one extended visit, but only after an in-person examination confirms the tooth and workflow are suitable.
- Immediate function — The final inlay functions immediately after bonding, although numbness lasts a few hours and mild cold, pressure, or bite sensitivity can occur for several days; allow 24–48 hours for a bite check before flying when possible.
- Key limitation — Thin, cracked, undermined, or heavily loaded cusps usually need an onlay or crown instead, while swelling, abscess, severe spontaneous pain, or suspected pulp disease must be treated before a definitive inlay.
- Korea distinction — Korean academic work supports access to digital CAD/CAM inlay workflows, but no high-quality studies show that inlay outcomes in Korea are superior to those in other countries; verify the individual clinic’s isolation, materials, milling or laboratory system, and overseas follow-up plan.
What Is an Inlay Filling?
An inlay filling is a custom-made indirect restoration that fits inside a prepared cavity in a tooth without covering its pointed chewing surfaces. It repairs moderate decay or a failed filling in a back tooth, restoring chewing function, tooth contact, and bite while preserving healthy structure. It is a minimally invasive dental procedure, usually completed with local anesthetic and bonding or cementation.
Who Is a Good Candidate for an Inlay Filling?
- Moderate posterior-tooth damage — Good candidates have decay, a failed filling, or an internal cavity in a premolar or molar that is too extensive for a predictable direct resin filling but still has sound, intact cusp tips.
- A restorable vital or treated tooth — The tooth needs enough healthy walls for an intracoronal restoration, with no evidence that the pulp, root, or supporting bone requires separate treatment.
- Defined functional goals — An inlay can restore chewing anatomy, contact with the adjacent tooth, and a stable bite while preserving more tooth structure than full coverage.
- Commitment to maintenance — Daily fluoride toothpaste, cleaning between teeth, caries-risk control, and dental reviews are essential because decay can recur at restoration margins.
An inlay is not appropriate when a cusp is thin, cracked, undermined, or subject to high bite force; an onlay, overlay, or crown provides cusp coverage in those cases. Active swelling, an abscess, severe spontaneous pain, suspected irreversible pulp disease, uncontrolled periodontal disease, or poor moisture isolation must be diagnosed and stabilized first. Clenching or grinding, especially in a root-canal-treated posterior tooth, raises the risk of ceramic partial-restoration failure and can change the material, design, or need for an occlusal guard, as reported in a clinical risk-factor study. Disclose allergies to local anesthetics, resin monomers, latex, metals, and restorative materials, as well as chemotherapy, severe immunosuppression, uncontrolled diabetes, or bleeding disorders before elective treatment.
How Is an Inlay Filling Performed?
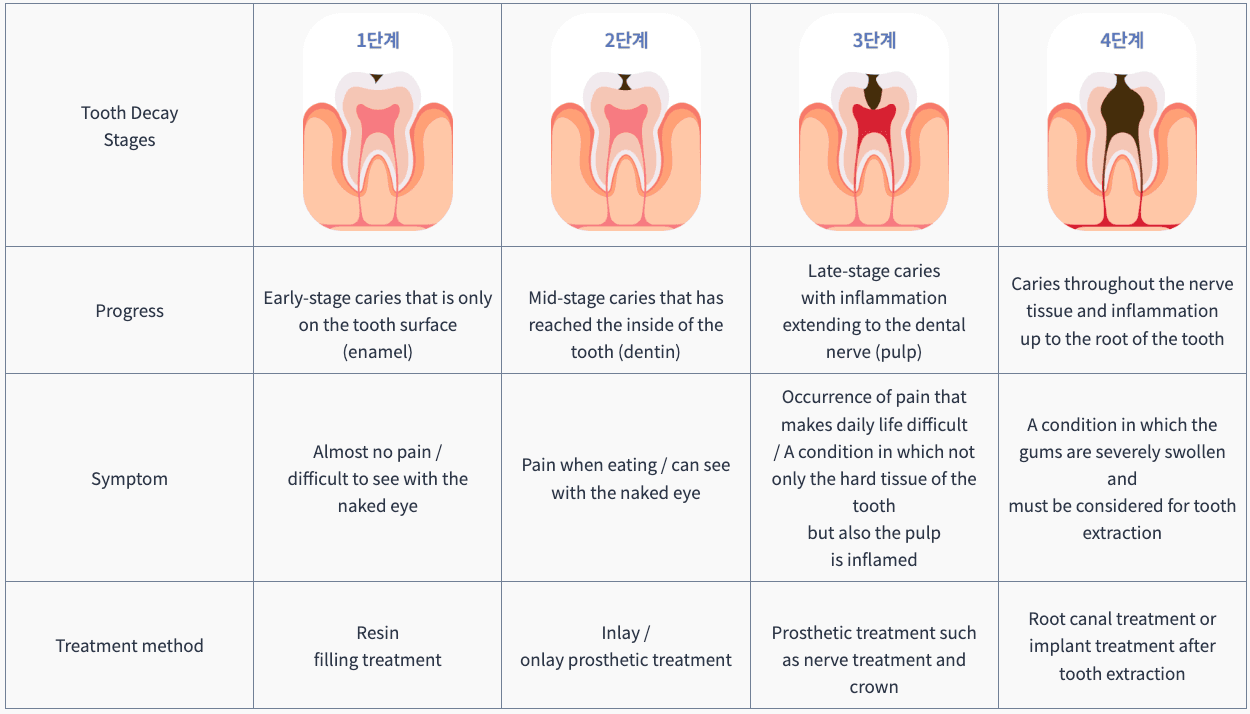
Material and fabrication method affect appearance, repair options, opposing-tooth wear, appointment schedule, and the bonding protocol. The correct choice depends on cavity size, remaining tooth structure, tooth location, bite, caries risk, and reliable isolation from saliva.
- Ceramic or glass-ceramic inlay — Tooth-colored ceramic, including lithium disilicate, offers color stability and wear resistance and is commonly adhesively bonded. Chipping, fracture, debonding, recurrent decay, and pulpal complications remain possible.
- Indirect composite-resin inlay — This tooth-colored option can be useful where repairability, stress absorption, or reduced wear against the opposing tooth matters. A systematic review found only two small randomized trials involving 138 inlays and no reliable evidence of overall superiority of ceramic or composite.
- Cast-gold inlay — Gold is long established and durable but visibly metallic. It is generally chosen when appearance is not the main priority and the clinical design suits the material.
- Conventional laboratory workflow — After tooth preparation, the dentist takes a physical impression or digital scan and places a temporary restoration. A laboratory fabricates the inlay before a separate try-in and bonding appointment.
- Digital CAD/CAM workflow — An intraoral scan guides computer design and milling either chairside or through a laboratory. Same-day completion is sometimes possible, but depends on the tooth, selected material, workflow, and whether examination identifies a crack, root-canal need, or gum problem.
Why Visit Korea for an Inlay Filling?
South Korea has documented academic activity in digital restorative dentistry, including CAD/CAM inlay work. This supports the presence of relevant digital workflows, not a country-wide guarantee of better treatment. Choose care based on the individual dentist’s diagnosis, isolation protocol, material selection, milling or laboratory quality control, and plan for care after departure.
- Digital-restorative research presence — Korean academic literature has reported work involving CAD/CAM restorations and inlays, supporting access to this area of restorative dentistry.
- Workflow verification matters — Ask whether the clinic uses a chairside or laboratory CAD/CAM route, which scanner and milling or laboratory system is used, and whether a temporary restoration is expected.
- Outcome evidence is limited — No high-quality studies directly compare outcomes for the same inlay treatment in South Korea versus other countries. Nationality or location is not a substitute for careful assessment of cracks, pulp health, bite, and remaining tooth structure.
- Long-term expectations require context — A systematic review and meta-analysis pooling ceramic inlays, onlays, and overlays estimated survival at about 92–95% at five years and 91% at ten years. These pooled figures do not predict an individual inlay’s lifespan because the studies combined different restoration types, materials, teeth, designs, and follow-up periods.
Key Information for International Patients
- Minimum stay — Plan 3–5 business days for a conventional laboratory-made inlay: diagnostics and preparation, scan or impression, fabrication, final try-in and bonding, and time for a bite review.
- Same-day option — A chairside CAD/CAM inlay can sometimes be completed in one extended visit. Do not book around this assumption until the dentist has examined the tooth and confirmed the selected material and workflow.
- Flight timing — There is no established universal no-fly interval after an uncomplicated inlay under local anesthetic. Do not travel while numb, and preferably allow 24–48 hours after final bonding for an occlusion and symptom check.
- Itinerary impact — Local-anesthetic numbness commonly lasts a few hours. Final placement functions immediately, but reserve time for a small adjustment if the bite feels high, food catches, or cold and pressure sensitivity persists.
- Remote follow-up — Before leaving, obtain the tooth number, radiographs or scans where available, restoration material, laboratory or CAD/CAM system, and cement or bonding details. Confirm who will respond if pain, a loose temporary, or bite problems occur after returning home.
Travel note: Keep flights flexible until definitive bonding is complete. Unexpected crack extension, pulpal exposure, periodontal treatment, or a need for root canal treatment can change both the restoration plan and travel schedule.
Which Are the Best Clinics in Korea for Inlay Filling?
Listed below are some of the best clinics in Korea for inlay filling.
1. Gangnam Gentle Dental Clinic
For an inlay filling, Gangnam Gentle Dental Clinic offers cavity assessment and restoration within a practice that emphasizes thorough consultation, personalized treatment, and providing only necessary care. You may also value its use of digital examination equipment, infection-prevention and sterilization systems, and emergency-care availability.
- URL: Gangnam Gentle Dental Clinic Website
- Location: Seocho-gu, Seoul
- Inlay and cavity care:
- Provides cavity treatment and fillings to restore teeth affected by decay.
- The clinic aims to reduce treatment time and the number of visits through its research and development efforts, where appropriate to your needs.
- Your visit:
- Dr. Travis Kim studied at Ohio State University and speaks fluent English, which may help if you prefer to discuss your treatment in English.
- Weekday and weekend opening supports varied schedules, and emergency dental treatment is available for urgent concerns such as severe pain, broken teeth, or abscesses.
- Related dental services:
- Offers root-canal treatment, gum treatment, wisdom-tooth extraction, clear aligners, and TMJ care.
- Implant options include 3D-guided implants, Straumann implants, and Osstem implants.
2. Minish Dental Hospital
For an inlay filling in Korea, Minish Dental Hospital may be worth considering if you need care for cavities alongside broader prosthodontic services in a large Gangnam facility with an in-house laboratory and dental technology company. Its team includes general-dental and veneer specialists, and the clinic reports treating cavities and providing prosthodontic restorations as part of individualized treatment planning.
- URL: Minish Dental Hospital Website
- Location: Gangnam-gu, Seoul
- Cavity and restoration care:
- Offers treatment for tooth decay and prosthodontic services, including restorations such as crowns, bridges, and dentures to support oral function.
- Molar Minish is presented as an option for extensive molar damage that seeks to minimize tooth reduction as an alternative to a conventional crown.
- Clinical resources:
- The facility spans 14 floors and reports using 19 advanced pieces of dental equipment.
- Minish operates an in-house laboratory and its own technology company; the clinic reports 84,504 hours of research and development.
- Related services:
- Provides periodontal therapy, orthodontic treatment, teeth whitening, implant treatment, and care for bruxism and TMJ concerns.
- Minish Veneers are custom veneers designed to require minimal or no tooth shaving, depending on your dental situation.
3. TU Dental Clinic (TU Dental)
For an inlay filling, TU Dental Clinic offers ceramic inlays and onlays for mid-stage tooth decay, using tooth-colored materials intended to closely match natural teeth while providing durability. The clinic describes a tooth-preserving approach and uses inlays, onlays, or zirconia crowns for deeper decay according to the extent of damage.
- URL: TU Dental Clinic (TU Dental) Website
- Location: Seocho-gu, Seoul
- Ceramic inlays and onlays:
- Ceramic inlays are used for mid-stage caries and are designed to provide natural-looking color and durable restoration.
- Ceramic onlays may be used when decay is larger or more widespread; the clinic describes them as having strong adhesion and a low risk of dislodgement.
- Early decay may be treated with tooth-colored resin, while deeper decay may call for an inlay, onlay, or zirconia crown.
- Tooth-preserving restorations:
- The clinic prioritizes preserving natural teeth and minimizing treatment discomfort.
- Zirconia crowns are offered for greater restoration needs; they are described as durable, similar in color to natural teeth, and requiring minimal tooth removal.
- Related care:
- Offers orthodontic plans tailored to tooth alignment, age group, and lifestyle, with several bracket options.
- Provides digitally planned full-case implants using 3D imaging, as well as partial implants for one or more teeth.
How Much Does an Inlay Filling Cost in Korea?
An Inlay Filling is listed at ₩400,000–₩600,000 (approximately US$300–$400). Individual quotes vary because the restoration plan must match the tooth’s defect, material requirements, and fabrication workflow.
| Procedure Price | Korean Won (₩) | USD ($) |
|---|---|---|
| Low Price | ₩400,000 | $300 |
| High Price | ₩600,000 | $400 |
Exchange rate as of 2026-09-06: 1 KRW = 0.000741 USD.
What Affects the Price?
- Restoration material — Ceramic or glass-ceramic, indirect composite-resin, and cast-gold inlays require different materials and handling protocols. Ceramic inlays often require adhesive bonding and careful conditioning, while cast-gold restorations use a different fabrication and cementation approach.
- Laboratory-made versus CAD/CAM workflow — A conventional laboratory-made inlay requires a scan or impression, temporary restoration, laboratory fabrication, and a later try-in and bonding visit. Chairside CAD/CAM uses intraoral scanning, digital design, and milling equipment, concentrating fabrication resources into an extended appointment when same-day treatment is feasible.
- Extent of tooth preparation and diagnostic needs — Removing decay or an old filling, assessing crack extension or pulp involvement, and preparing a larger or more complex cavity requires additional clinical time. Targeted radiographs, vitality testing, or a revised plan are needed when symptoms or examination findings raise concern for root-canal treatment or a restoration requiring cusp coverage instead.
- Bonding, fit, and bite adjustment requirements — Final placement requires checking margins, contact points, chewing anatomy, and occlusion before bonding or cementation under reliable moisture control. A high bite, difficult contact adjustment, or persistent sensitivity can require further chair time and an in-person review after placement.
Cost tip: Request an itemized quote that states what is included, such as diagnostics, tooth preparation, scan or impression, temporary restoration when required, laboratory or CAD/CAM fabrication, final bonding or cementation, and bite-review visits.
The US$300–$400 conversion is approximate, based on the exchange rate dated 2026-09-06; check the exchange rate again when budgeting.
Inlay Filling From Start to Finish
- Remote contact and preliminary review — Send recent dental radiographs when available, photographs, the tooth’s symptoms, prior root-canal history, grinding history, medication list, allergies, and relevant medical conditions. Request confirmation of English-language or virtual consultation availability. Remote review cannot establish that an inlay is suitable.
- In-person diagnosis — The dentist examines the tooth, gums, bite, caries risk, and remaining structure. Vitality testing and targeted bitewing or periapical radiographs are used when clinically indicated to assess recurrent decay, root-end disease, and bone support.
- Treatment-plan confirmation — The dentist determines whether the defect remains within the tooth and leaves strong cusps. A crack, weak cusp, pulp problem, or deep disease can change the plan to an onlay, crown, or endodontic treatment.
- Local anesthesia and tooth preparation — Local anesthetic is commonly used. The dentist removes decay and failing filling material, evaluates for crack extension or pulp exposure, and shapes the cavity for the selected indirect restoration.
- Scan or impression and temporary — A digital intraoral scan or conventional impression records the preparation. With laboratory fabrication, a temporary restoration usually protects the tooth between appointments.
- Fabrication — A dental laboratory or CAD/CAM system produces the ceramic, composite, or gold inlay. A chairside CAD/CAM workflow can reduce the number of visits when clinically appropriate.
- Try-in and definitive bonding — The dentist checks margins, fit, contact points with neighboring teeth, chewing anatomy, and occlusion. The tooth and restoration are conditioned according to the material, then bonded or cemented under moisture control, adjusted, and polished.
- Discharge and in-country review — Receive written aftercare instructions and return promptly for a high bite, food trapping, a lost temporary, or ongoing symptoms. Schedule a review before departure when possible.
- Overseas follow-up — Contact the Korean clinic with clear photos and a symptom description if concerns arise at home, and arrange local dental assessment for persistent pain, swelling, fracture, or bite dysfunction.
Alternatives to an Inlay Filling
The main tradeoff is between conserving tooth structure and providing enough protection for weakened cusps or diseased pulp. A direct filling is more conservative for a smaller defect; an onlay or crown becomes more protective when an intracoronal inlay would leave the tooth structurally vulnerable.
Resin Filling
- Best fit — A resin filling is often suitable for smaller cavities where a direct restoration can reliably restore contact, contour, and bite.
- Tradeoff — It is completed directly in the mouth, usually in one visit, but may be less predictable for a larger or more complex posterior defect.
Onlay or Crown
- Best fit — An onlay, overlay, or dental crown is considered when cusps are cracked, thin, undermined, or exposed to high chewing forces.
- Tradeoff — Cusp coverage offers greater protection but generally requires more tooth reduction than an inlay.
Root Canal Treatment
- Best fit — Root canal treatment is required when the pulp is irreversibly inflamed, necrotic, or infected.
- Tradeoff — It treats disease inside the tooth; it does not replace the final restoration. The tooth then needs a restoration chosen according to remaining structure and bite forces.
Dental Implant
- Best fit — A dental implant is considered only when the tooth cannot be restored or has already been lost.
- Tradeoff — It replaces a missing tooth rather than preserving the natural one and is not a routine alternative for a restorable tooth.
How Can I Prepare for an Inlay Filling?
- Records and disclosure — Send recent radiographs, dental records, a full medication and supplement list, allergies, prior anesthesia reactions, and details of pregnancy, diabetes, bleeding history, heart conditions, joint replacement, immunosuppression, cancer treatment, or prior root-canal treatment.
- Anticoagulants and antiplatelets — Do not independently stop aspirin, clopidogrel, warfarin, apixaban, rivaroxaban, dabigatran, or similar medicines. Changes require direction from the prescribing clinician and dentist, consistent with ADA guidance on dental care and these medicines.
- Antibiotics — Do not self-start antibiotics or use leftover tablets. Routine preventive antibiotics are not indicated for a straightforward inlay; selected patients with the highest-risk cardiac conditions need individualized assessment under antibiotic prophylaxis guidance.
- Food and sedation — Eat normally before treatment under local anesthetic unless the clinic says otherwise. Follow the dental or anesthesia team’s fasting, medication, escort, and activity instructions exactly if oral, inhaled, IV, or general-anesthesia sedation is planned.
- Oral preparation — Brush carefully and clean between teeth before appointments. Tell the clinic about swelling, fever, worsening spontaneous pain, or a broken filling before travel rather than assuming the case can proceed as scheduled.
- Smoking and alcohol — Avoid tobacco and vaping where possible and avoid alcohol around any sedation appointment. Tobacco use harms oral health and can complicate long-term dental maintenance.
- Travel arrangements — Book accommodation near the clinic for conventional treatment, avoid a non-changeable departure immediately after final bonding, and arrange an adult escort when sedation is used.
Travel note: Bring any existing night guard. A grinding history can alter the inlay design, material choice, and need for a new occlusal guard.
Confirm the treating dentist’s clinic-specific requirements; individualized instructions take precedence over this general guidance.
Aftercare Advice
Protect the new restoration from biting trauma while numb and arrange prompt review for a bite that does not feel normal.
- Numbness and eating — Do not chew until local-anesthetic numbness has fully resolved; this prevents biting the cheek, lip, or tongue. After final bonding, the restoration functions immediately.
- Temporary restoration — Avoid sticky foods and very hard chewing on a tooth with a temporary inlay. Contact the clinic promptly if the temporary loosens, fractures, or comes out.
- Sensitivity and bite — Mild cold, pressure, gum, or bite sensitivity can occur for several days after preparation or bonding. Request adjustment promptly for a high bite, sharp pain on biting or release, repeated food packing, or inability to chew comfortably.
- Daily cleaning — Brush twice daily with fluoride toothpaste and clean between teeth daily. This helps limit recurrent decay around restoration margins.
- Warning signs — Seek dental assessment for increasing or spontaneous throbbing pain, pain that wakes you, facial or gum swelling, fever, drainage or a bad taste, persistent numbness, or a loose, cracked, or lost restoration. Severe swelling with breathing or swallowing difficulty is an emergency.
- Final review — Complete an in-person review before international departure when possible, especially after laboratory bonding. Functional appearance is immediate, but persistent symptoms require examination rather than self-treatment.
Follow the treating doctor’s instructions over general advice and contact the clinic promptly when anything appears wrong.
Frequently Asked Questions
Related Blogs

Implant in Korea: Treatment Steps, Recovery, Travel Timing, and Alternatives
Dental implants replace missing or non-restorable teeth through staged assessment, fixture placement, healing, and a final crown, bridge, or denture. In Korea, quoted costs are ₩1,700,000–₩2,800,000 (about US$1,300–$2,100), with 7–14 days typically needed for placement follow-up and 3–6 months before definitive restoration.
Updated: Sep 19, 2026

Teeth Crown in Korea: Types, Treatment Steps, Travel Timing, and Aftercare
Dental crowns restore weakened or damaged teeth with full coverage; treatment includes assessment, tooth preparation, scanning or impressions, temporary or CAD/CAM fabrication, fitting, and bite checks. In Korea, crowns cost ₩600,000–₩1,100,000 (about US$400–$800), and international patients should remain for final fitting and adjustment.
Updated: Sep 18, 2026

Dental Bridge in Korea: Types, Treatment Timeline, Travel Planning, and Aftercare
Dental bridges replace one or more missing teeth using crowns, bonded wings, implants, or a combination, with the final design determined by tooth, gum, bone, and bite health. The article explains candidate criteria, bridge types, treatment steps, Korea travel planning, aftercare, alternatives, and the need for local follow-up.
Updated: Sep 18, 2026

All-ceramic Veneers in Korea: Types, Treatment Steps, Travel Planning, and Aftercare
All-ceramic veneers are bonded after assessment of enamel, gums, bite, and cosmetic goals, with preparation, laboratory fabrication or CAD/CAM milling, try-in, bonding, and bite adjustment. International patients can review candidate criteria, Korea travel planning, minimum stays, records to obtain, alternatives, preparation, and aftercare requirements.
Updated: Sep 18, 2026
Clinics offering Inlay Filling

Minish Dental Hospital: Korea's Premier Dental Clinic Offering Advanced Treatments and Personalized Care
Sinsa

Gangnam Gentle Dental Clinic: Your Trusted Dental Care Provider in Korea Offering Comprehensive Services with Optimal Comfort and Safety
Sinnonhyeon Station

Experience Advanced Dental Care at TU Dental Clinic (TU Dental) in Korea: Top-Rated Orthodontics, Implants, and Esthetic Treatments
Gangnam Station

365SeoulOneTop Dental Clinic Korea | Specialist Implants, Sedation, Cosmetic Dentistry & Invisalign in Hwagok
Hwagok